Understanding the Anion Gap?
The anion gap is a derived value that assists clinicians determine the difference between commonly measured electrolytes in the blood. It is most often used as a helpful clue in metabolic acidosis, where it can help identify whether excess acids or other unmeasured anions are present.
At its core, the anion gap shows the relationship between sodium, chloride, and bicarbonate. Because the body maintains electrical neutrality, the measured positive and negative charges should remain equal. When they do not, the gap can suggest an electrolyte imbalance or another metabolic abnormality that needs further evaluation.
The anion gap is not a measured value. Instead, it is a computed approximation that supports acid-base balance evaluation and broader acid-base disorders assessments. In practice, it is best viewed as a screening and clinical interpretation tool rather than a independent diagnosis.
In what way the Anion Gap Calculator Works
An anion gap calculator applies a straightforward equation built on typical lab values. A common approach is:

Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also include potassium, even though many clinicians omit it because the value typically contributes little to routine interpretation. If potassium is included, the formula becomes:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
This computation relies on blood electrolytes from a serum chemistry panel or more comprehensive metabolic panel. The result helps reveal whether there may be a accumulation of acids or another shift in measured ions. Since bicarbonate is often reduced in acidosis, the calculator is especially useful in the assessment of serum bicarbonate values and related acid-base interpretation.
The calculator is a useful diagnostic aid because it transforms routine laboratory values into a more informative assessment of acid-base balance. When used properly, it supports clinical decision making by identifying patterns that deserve further attention.
Typical Anion Gap vs Elevated Anion Gap Acidosis
Understanding the contrast between normal anion gap metabolic acidosis and increased anion gap metabolic acidosis is essential for precise interpretation. Each are forms of metabolic acidosis, but they result from different mechanisms.
In typical anion gap metabolic acidosis, the bicarbonate drops, but the loss is usually matched by a gain in chloride. This pattern is often called chloride-responsive acidosis. The anion gap persists within the expected range because the decrease in one measured ion is balanced by an increase in another.
In high anion gap metabolic acidosis, bicarbonate decreases and there are additional unmeasured acids in the blood. These acids leave behind their anions, which increases the gap. This pattern indicates a larger accumulation of unmeasured anions and typically requires a search for causes such as lactic acidosis, ketoacidosis, renal dysfunction, or toxic exposures.
From a clinical standpoint, the distinction matters because it narrows the differential diagnosis. A typical anion gap pattern leans toward causes of bicarbonate loss, while a increased anion gap pattern leans toward acid production, acid retention, or impaired clearance.
Interpreting the Result
Reading an anion gap result demands more than looking at the number to a reference range. The first step is to check whether albumin is low, because albumin is a major unmeasured anion and heavily influences the value. When albumin is reduced, the gap may look falsely normal even when clinically important acidosis is present.
At this point the corrected anion gap becomes important. The correction adjusts the measured result upward when albumin is low, improving diagnostic accuracy. This process is often called albumin adjustment or anion gap correction, and it can reveal hidden high-gap acidosis that would otherwise be missed.
The delta gap is another helpful concept. It compares the change in anion gap to the change in bicarbonate and can uncover mixed acid-base disorders. For example, a patient may have high anion gap acidosis plus a concurrent metabolic alkalosis, which can make the bicarbonate appear less reduced than expected.
Proper interpretation always integrates the calculator result with the patient’s clinical assessment. Symptoms, history, medications, renal function, and other laboratory findings matter. A single number rarely gives the full picture.
Useful interpretation questions include:
- Is the anion gap truly elevated after albumin correction? Does the bicarbonate change follow the expected pattern? Are there signs of mixed acid-base disorders? Does the clinical context suggest lactate elevation, ketones, renal impairment, or toxins?
Frequent Reasons for Elevated Anion Gap
An elevated anion gap usually means that additional acids are present or that acid clearance is impaired. The main causes include lactic acidosis, ketoacidosis, renal failure, uremia, and certain toxins.
Lactic acidosis develops when lactate accumulates, often due to tissue hypoperfusion, severe illness, seizures, or other states of increased anaerobic metabolism. As lactate is an unmeasured anion, the anion gap rises as bicarbonate falls.
Ketoacidosis may occur with diabetes, prolonged fasting, or alcohol-related metabolic states. Ketone bodies serve as unmeasured acids, producing a high anion gap metabolic acidosis that often requires urgent treatment.
Renal failure and uremia decrease the body’s ability to excrete acid and retain normal acid-base homeostasis. As retained acids accumulate, the anion gap can rise significantly.
Toxins are another key category. Certain ingestions can cause profound acid-base disruption and may present with an increased gap. In these cases, the calculator is simply one part of the evaluation, not the entire diagnosis.
Additional causes can occur, but these major categories explain many clinically significant cases of elevated anion gap metabolic acidosis. Recognizing the pattern helps guide targeted testing and timely treatment.
Medical Context and Caveats
The anion gap is helpful, but it has important limitations. The result must always be assessed alongside the blood gas, serum chemistry panel, and the wider clinical context. It cannot substitute for bedside judgment or the full evaluation of acid-base disorders.
One limitation is variation in the laboratory reference range from one lab to another. Multiple analyzers, different measurement methods, and different reporting or omission of potassium can all influence the value. That means a “normal” number in one setting may not correspond precisely to another setting.
Another limitation is the effect of albumin. Without correction, the anion gap may miss clinically meaningful abnormalities. Also, the gap does not identify the exact acid responsible; it only suggests that unmeasured anions may be present.
A blood gas helps establish acid-base status by showing pH and carbon dioxide, while the serum chemistry panel provides the electrolyte data needed for calculation. Together, these results aid stronger diagnostic interpretation. The best use of the calculator is as part of a structured patient evaluation, not as a substitute for it.
Important pitfalls include:
- Believing a normal gap excludes all clinically significant acidosis Overlooking low albumin when evaluating the result Failing to compare the gap with bicarbonate using the delta gap Using the calculator without considering the blood gas and clinical context
Stepwise Illustrative Calculations
An illustrative calculation helps show how the formula works in practice. Consider these lab values:
- Sodium: 140 Chloride: 102 Bicarbonate: 18
Using the formula, the anion gap is:
140 − (102 + 18) = 20
This finding suggests a elevated anion gap metabolic acidosis, assuming the local reference range is lower than 20. The next step would be to assess the clinical picture for causes such as lactic acidosis, ketoacidosis, renal failure, or toxins.
Now add albumin to the picture. If albumin is low, the measured gap may underestimate the problem. A corrected anion gap can be calculated using albumin adjustment to better estimate the true burden of unmeasured anions.
For a second illustration, imagine a patient with the following values:
- Sodium: 138 Chloride: 112 Bicarbonate: 18
The calculation is:
138 − (112 + 18) = 8
This pattern may reflect a normal anion gap metabolic acidosis pattern, especially if bicarbonate is low and chloride is relatively high. In that setting, the interpretation may point more toward bicarbonate loss rather than excess unmeasured acids.
In a more advanced case, the corrected bicarbonate and the delta gap can be used together. If the anion gap is elevated but bicarbonate is not as low as expected, a mixed disorder may be present. That kind of interpretation is especially valuable when acid-base balance is complex and multiple processes overlap.
These examples show why calculator use is only the first step. The final interpretation depends on whether the numbers match the clinical story and whether additional testing supports the same conclusion.
FAQ for the Anion Gap Calculator
What does an Anion Gap Calculator assess?
An Anion Gap Calculator measures the variation between key measured electrolytes, usually sodium, chloride, and bicarbonate. The result estimates whether there are excess unmeasured anions in the blood and supports the assessment of metabolic acidosis and other acid-base disorders.
What is a normal anion gap range?
The normal anion gap range is based on the laboratory reference range used by the testing method. Because labs differ, it is best to read the result using the reference range provided with the patient’s serum chemistry panel and the overall clinical context.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anion. https://anion-gap-test181.novacrestiq.com/posts/how-to-apply-an-anion-gap-calculator-for-acid-base-diagnostic-differentiation When albumin is low, the measured anion gap may seem falsely normal. Correcting for albumin enhances diagnostic accuracy and helps reveal hidden metabolic acidosis.
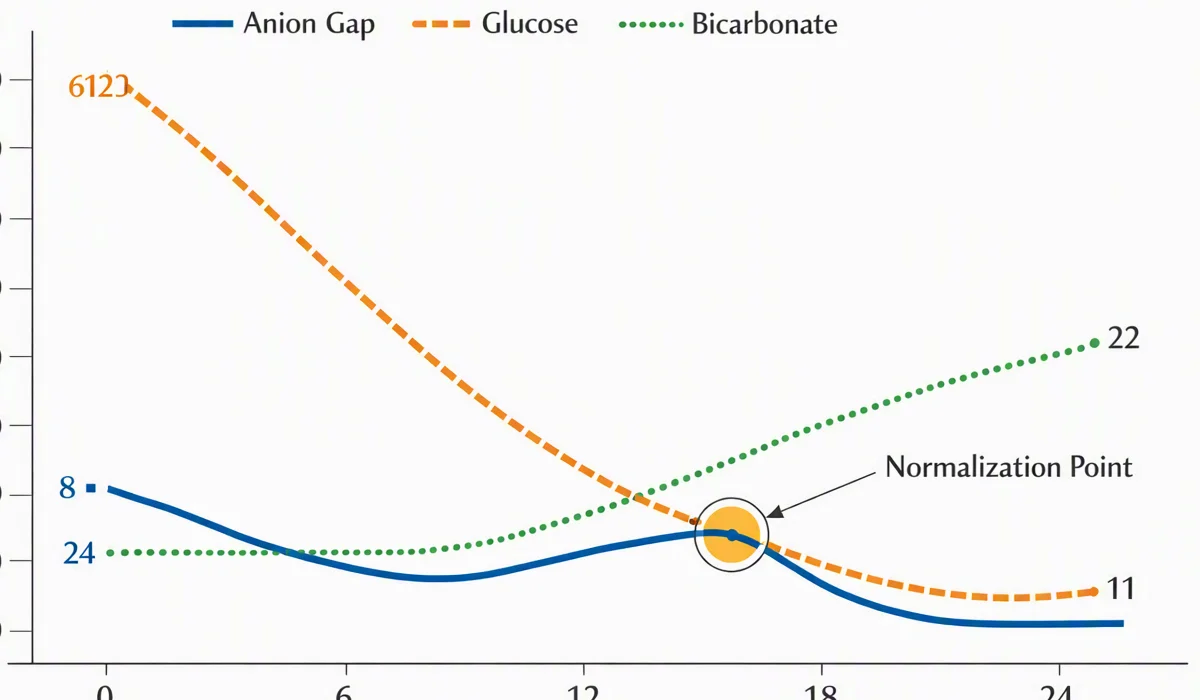
What can cause a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxins. These conditions increase unmeasured anions or reduce acid clearance, which widens the anion gap and lowers bicarbonate.
How does the delta gap used in anion gap interpretation?
The delta gap compares the change in anion gap with the change in bicarbonate. It helps identify mixed acid-base disorders, such as high anion gap metabolic acidosis combined with metabolic alkalosis or a normal anion gap process. This helps make interpretation more precise during patient evaluation.