Understanding the Anion Gap?
The anion gap is a derived measurement that helps clinicians analyze acid-base disorder types, especially when assessing metabolic acidosis. It estimates the difference between measured positively charged and negatively charged electrolytes in the blood. In routine practice, the most common version uses serum sodium, serum chloride, and serum bicarbonate from an electrolyte panel.
This calculation is a useful diagnostic tool because it helps reveal unmeasured acids that are not obvious from individual laboratory values. A normal result often suggests one pattern of acid-base balance, while an elevated result may point toward acid accumulation from a systemic problem.
At its core, the anion gap is a type of anion gap calculation used in serum chemistry to improve clinical interpretation. It does not diagnose a disease by itself, but it helps narrow the differential diagnosis and supports clinical decision making.
Typical components include:
- Sodium as the main measured cation Chloride as the primary measured anion Bicarbonate as an additional major measured anion
Because the balance reflects multiple charged particles, any electrolyte imbalance can change the result. That is why understanding the context of the anion gap matters as much as the number itself.
Reasons why Corrected Sodium Is Significant
Corrected sodium becomes important when the measured sodium may not reflect the patient’s true water and solute status. This is most relevant in hyperglycemia, where high glucose shifts water out of cells and can lower the measured sodium concentration. In that case, a corrected value gives a more accurate estimate of the underlying sodium level.
Another important issue is pseudohyponatremia, where the sodium appears low because of certain laboratory measurement effects, not because the body truly has low sodium. In these cases, the apparent abnormal sodium can alter the anion gap and weaken diagnostic accuracy.

Serum glucose is therefore an key companion value when interpreting sodium in acute illness. If glucose is significantly elevated, the sodium should be interpreted using a correction factor before relying on the anion gap for clinical interpretation.
Why does this matter? Because a false sodium value can change the math and alter the https://anion-gap-reader975.cloudhinter.com/posts/what-is-a-combined-acid-base-disorder-with-increased-anion-gap estimated difference between measured ions. That can affect whether the result appears normal, mildly abnormal, or consistent with high anion gap metabolic acidosis.
Correcting sodium helps preserve diagnostic accuracy and improves better recognition of a true metabolic derangement. It also improves risk stratification in patients with acute illness, especially when serum chemistry is changing rapidly.
How the Anion Gap Calculator Works
An anion gap calculator applies a simple formula built on the measured blood chemistry and, when needed, an albumin correction. The usual anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians prefer a version that includes potassium, but the sodium-based form is the most common. Because bicarbonate is one of the key inputs, a low value often signals metabolic acidosis or another acid-base disturbance.
When sodium is abnormal, a corrected sodium should be considered first. Then the calculator can generate a more meaningful result. This is where the anion gap calculator becomes more than a math tool; it becomes a practical aid for clinical decision making.
Albumin correction may also be applied because albumin is a major unmeasured anion. Low albumin can hide an elevated gap, making the patient look less acidotic than they really are. In many cases, this produces an albumin-corrected anion gap that more closely reflects the actual acid-base state.
In short, the calculator combines the measured numbers with correction logic to improve interpretation. That matters because acid-base problems are often part of broader systemic illness, and the correct pattern can direct timely workup and treatment.
Input Requirements for the Calculator
A dependable result depends on the correct inputs. At minimum, an anion gap calculator needs:
- Sodium Chloride Bicarbonate Albumin, when performing albumin correction
Many calculators also accept glucose so they can estimate corrected sodium when hyperglycemia is present. This enhances the interpretation of the electrolyte panel and helps minimize error caused by dilutional changes.
These inputs come from routine laboratory test results. Because the values are interdependent, the context of the collection is important. For example, a patient with dehydration, acute infection, or kidney injury may show a different pattern than a stable outpatient with no electrolyte imbalance.
If bicarbonate is low, the tool may suggest a concerning acid-base pattern. If albumin is low, the uncorrected value may miss the severity of the disturbance. If sodium is altered by glucose or measurement artifact, the result can be misleading unless the correction is applied.
That is why a calculator is best understood as a diagnostic tool rather than a standalone answer. It brings together several laboratory values into a more coherent assessment of acid-base balance.
How to Understand a Standard vs Elevated Anion Gap
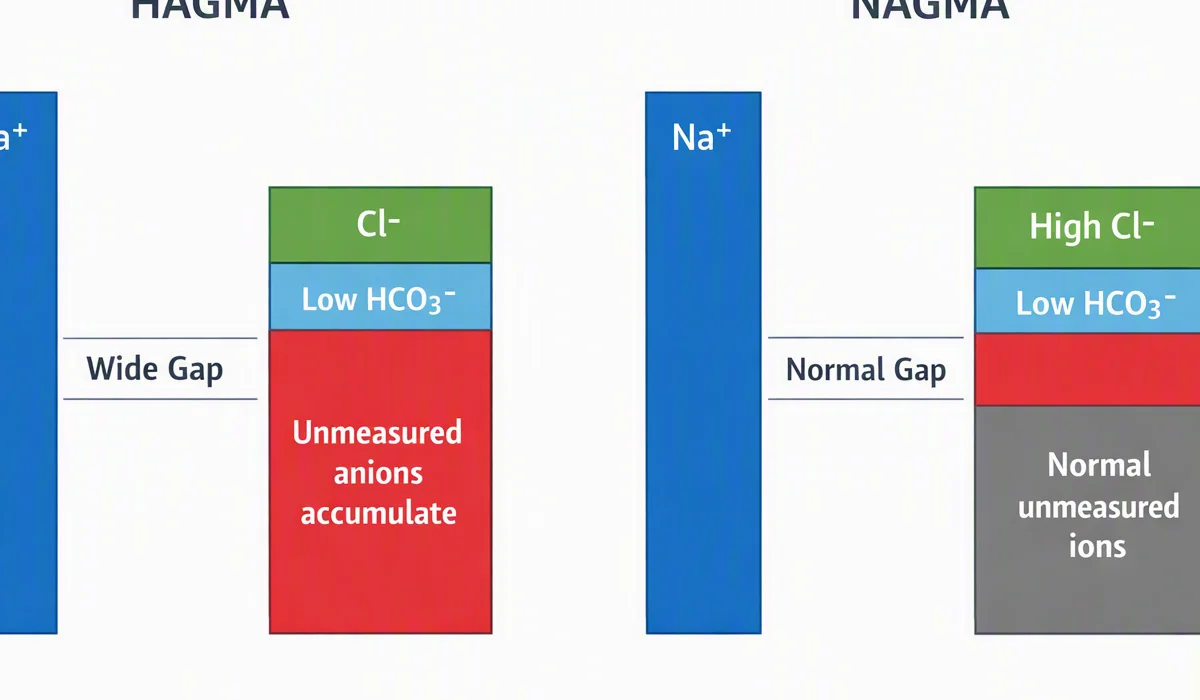
A normal anion gap usually implies that bicarbonate loss is being offset by chloride gain, a pattern often seen in normal anion gap metabolic acidosis. In this setting, the total gap may remain within expected limits even though the patient is acidotic.
An high anion gap implies unmeasured acids are accumulating. This points toward high anion gap metabolic acidosis and should lead to evaluation for sources of acid accumulation. The key is to interpret the gap together with the bicarbonate level, sodium correction, and the overall clinical picture.
This distinction is important because two patients can both have low bicarbonate, yet one may have a normal gap and the other a high gap. Those are different acid-base disorders with different causes and different workups.
Lactic acidosis is one of the most important causes of an elevated gap. It often suggests tissue hypoperfusion, severe infection, or other forms of systemic illness. In contrast, a normal gap with low bicarbonate may suggest gastrointestinal bicarbonate loss or renal tubular issues.
Corrected sodium can alter whether the result appears normal or elevated. That is why the calculator should be used with awareness of clinical interpretation and not just as a numeric shortcut.
Common Causes of an Elevated Anion Gap
Several conditions can produce an abnormal result, and the list of possible diagnoses is extensive. The primary causes include:
- Elevated lactate Ketone buildup Renal failure Poisonous alcohols Severe infection
Ketone buildup happens when ketone production increases rapidly, as in diabetic crises or severe starvation states. This can create substantial acid accumulation and a clearly elevated gap.
Renal insufficiency impairs the body’s ability to clear acids, so unmeasured anions collect in the blood. The result is often a metabolic derangement that becomes more obvious as kidney function worsens.
Alcohol toxins are an additional critical cause because they can lead to both an elevated gap and other osmotic abnormalities. In these cases, checking osmolality alongside the anion gap can give valuable clues.
Systemic infection can stimulate lactic acid production through poor perfusion and altered metabolism. This often creates a high-gap pattern and requires urgent recognition.
These conditions are important because they often represent time-sensitive illness. The anion gap, especially when combined with corrected sodium and albumin correction, helps identify the pattern early and supports appropriate next steps.
Detailed Example Calculation
Here is a straightforward sample calculation that shows how adjusted sodium alters the clinical interpretation.
Imagine a patient has the following measurements:
- Measured sodium: 128 Chloride: 96 Bicarbonate: 18 Albumin: low Serum glucose: very elevated
As glucose is high, beforehand estimate the corrected sodium formula using a common adjustment approach. The precise correction factor can change by method, but the purpose is the same: raise the sodium upward to match the glucose-related shift in water.
Following correction, assume sodium rises from 128 to 133. Now use the anion gap formula:
Anion gap = 133 − (96 + 18) = 19
The calculated anion gap is increased. If albumin is low, the albumin-adjusted anion gap may be even higher, increasing the concern for metabolic acidosis.
Clinical meaning: this pattern is more suggestive with raised anion gap metabolic acidosis than with a normal-gap process. In light of the presentation, the differential may include lactic acidosis, ketotic acidosis, renal failure, or toxic alcohol ingestion.
This case shows why corrected sodium is not a minor technicality. It can alter the final number enough to change the diagnostic direction and improve the usefulness of the anion gap calculator in real practice.
Constraints and Practical Considerations
Although a carefully built calculator has restrictions. The primary issue is the albumin effect, since low albumin can mask an increased gap. If albumin is not taken into account, the interpretation may miss the severity of the acid base problem.
Lab variation also matters. Various analyzers, sample handling issues, and timing differences can change the reported laboratory values. Slight shifts in sodium, chloride, or bicarbonate may alter the calculated gap enough to affect interpretation.
Another limitation is that the number alone does not define the complete acid-base status. You still need the clinical picture, medication history, kidney function, glucose level, and sometimes additional testing such as lactate or ketones. The gap should be one piece of a larger assessment.
The best use of the calculator is in clinical context. If the patient has shock, confusion, dehydration, or suspected poisoning, the result carries greater weight. If the patient is otherwise stable, the finding may require a more measured evaluation.
In other words, the calculator improves diagnostic accuracy, but it does not replace judgment. It helps clinicians make sense of an abnormal sodium value, identify possible acid accumulation, and link the number to the likely cause of illness.
FAQ About Anion Gap and Corrected Sodium
What is an anion gap calculator with corrected sodium?
An anion gap calculator with corrected sodium is a diagnostic tool that uses serum sodium, chloride, and bicarbonate, while adjusting sodium when it is abnormal due to factors like hyperglycemia. It helps deliver a more accurate estimate of the anion gap and improves clinical interpretation of acid-base balance.
Why do you correct sodium before interpreting the anion gap?
You correct sodium because a falsely low measured sodium can skew the anion gap calculation. This is common in hyperglycemia and sometimes pseudohyponatremia. Using a corrected value helps preserve diagnostic accuracy and prevents misclassification of metabolic acidosis.
How do you calculate the anion gap from lab values?
Use the formula sodium minus chloride plus bicarbonate, written as anion gap = sodium − (chloride + bicarbonate). When sodium is abnormal, use a correction factor first. If albumin is low, consider albumin correction to estimate an albumin-corrected anion gap.

When is the anion gap elevated but still misleading?
The gap can be raised yet still misleading when sodium is not corrected, when albumin is low, or when lab variation affects the result. It can also be hard to interpret if the patient has mixed acid-base disorder patterns. In those cases, the number should be interpreted with the full clinical context and, when needed, osmolality and other tests.
Do you always need to correct albumin when interpreting the anion gap?
It is not always required, but it is often helpful. Because albumin is a major unmeasured anion, low levels can hide a true acid-base problem. When you suspect metabolic acidosis, especially high anion gap metabolic acidosis, using albumin correction can improve the value of the result and support better clinical judgment.