What Is the Anion Gap and How Is It Computed?
The anion gap is a calculated value that helps clinicians assess acid-base balance and recognize an underlying metabolic acidosis. It reflects the difference between the major measured cations and anions in the blood. In practical terms, it is calculated from the routine electrolyte panel using sodium, chloride, and bicarbonate.
The classic anion gap formula is:
anion gap = sodium - (chloride + bicarbonate)
Because this is a calculated value, it relies on the accuracy of the underlying lab numbers. A unexpectedly high result suggests that unmeasured anions are present in the bloodstream. These may include organic acids, toxic metabolites, or other compounds that create an electrolyte disturbance and push the body toward an acidotic state.
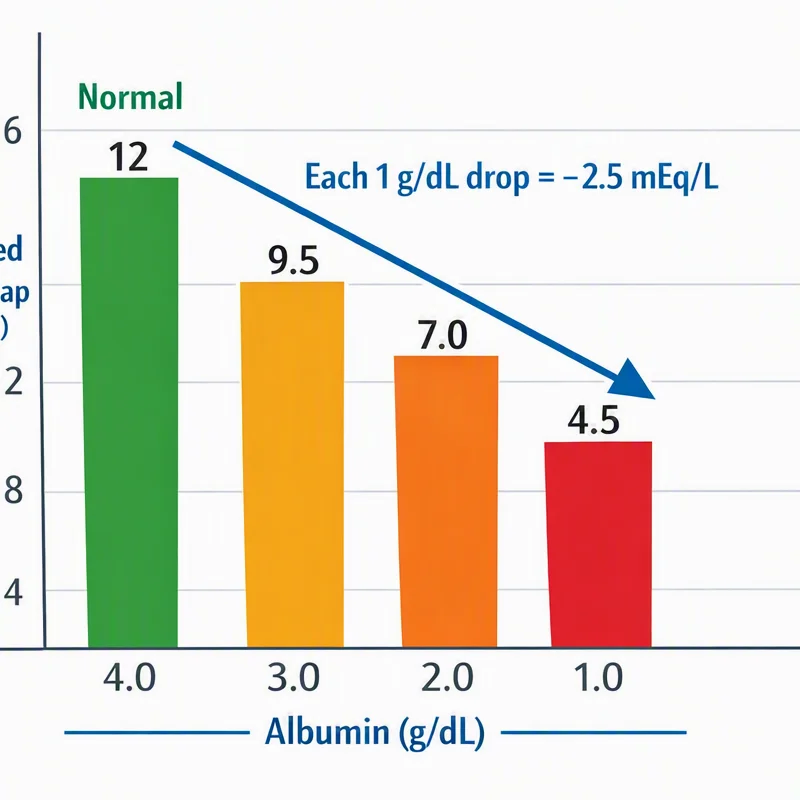
Most clinicians also consider the role of albumin, the main unmeasured anion in blood. Low albumin can lower the apparent anion gap, so the raw number may underestimate the severity of an anion gap elevation. That is why interpretation always depends on the clinical setting, not the number alone.
The key idea is simple: the anion gap is not a diagnosis. It is a diagnostic clue that can point toward a process such as lactic acidosis, ketoacidosis, renal dysfunction, or toxin-related acidosis.
How an Anion Gap Calculator Helps Interpret Results
An Anion Gap Calculator simplifies the process of working with the formula consistently and quickly. Instead of estimating the calculation by hand, a clinician or patient can enter the relevant laboratory values and get an immediate result. This can be useful when trying to decide whether a reported lab pattern fits a normal reference interval or suggests an abnormal acid base process.
Beyond simple calculation, the best use of an Anion Gap Calculator is clinical interpretation. A number by itself rarely answers the full clinical question. The result should be viewed within the broader picture with symptoms, vital signs, medications, exposure history, and the rest of the chemistry panel.
Many calculators also include albumin correction. This matters because a low albumin level can hide a true gap. Correcting for albumin improves laboratory interpretation and helps avoid missing an important metabolic derangement. If albumin is low, a patient may have significant high anion gap metabolic acidosis even when the uncorrected value appears only mildly elevated.
Using a calculator can also help separate a true metabolic problem from a reporting issue. For example, an electrolyte panel may show a borderline gap, but the presence of low bicarbonate, elevated lactate, or an abnormal blood gas may reveal a more serious process. The calculator therefore supports a broader pattern-recognition approach instead of replacing clinical judgment.
In toxin evaluation, the calculator can serve as an early screen. If the gap is elevated, clinicians may think about exposures that generate unmeasured anions. If the gap is normal but suspicion remains high, further testing may still be needed.
Can Poisonous substances Elevate the Anion Gap?
Absolutely. Certain harmful substances can raise the anion gap by producing acids, impairing metabolism, or triggering accumulation of poisonous metabolites. This is a typical cause of increased anion gap metabolic acidosis. In these cases, the body holds on to acidic compounds that are not directly measured on a standard panel, so the gap grows as bicarbonate drops.
A harmful ingestion often causes several changes at the same time. The patient may have nausea, emesis, dizziness, mental clouding, tachypnea, or increasing exhaustion. Lab results may show low bicarbonate, rising chloride changes, and an increased anion gap. The specific pattern depends on the substance involved and how long ago the exposure occurred.
The mechanism is often a form of metabolic acidosis caused by too much acid production or poor acid elimination. Some exposures directly produce acids, while others impair cellular respiration, creating lactate buildup or other downstream effects. In all cases, the gap is an indicator of accumulation of unmeasured acidic substances.
Crucially, toxin-related acidosis is not limited to one poison. Several agents can lead to a similar chemistry pattern, which is why exposure history and targeted testing are important. The anion gap provides an early clue, but not the full diagnosis.
Typical Harmful Sources of a High Anion Gap
Several toxins are traditionally linked to a high gap. The main include methanol, ethylene glycol, and salicylates, along with disorders that produce lactic acidosis. These problems can be life-threatening and may present with nonspecific poisoning symptoms.
Methanol is highly dangerous because it is metabolized into acidic compounds, including formic acid. This leads to acidosis and may also affect vision and the central nervous system. An elevated gap in the setting of exposure history should raise urgent concern.
Ethylene glycol, found in some antifreeze products, is metabolized into glycolic acid and other acids. These toxic metabolites can drive a sharp rise in the anion gap and create kidney injury, neurologic changes, and worsening acidosis.
Salicylates can produce a mixed and evolving picture. Initially, respiratory alkalosis may dominate, but as toxicity progresses, a high gap metabolic acidosis may emerge. Because of this, the lab pattern can change over time and may not be obvious on a single sample.
Lactic acidosis is another major contributor to a high gap. Although not always caused by an external toxin, it can result from impaired tissue oxygen use, shock states, seizures, or severe poison exposure. In toxin evaluation, rising lactate is a major clue that cells are struggling to generate energy normally.
Further poisonings can also contribute, but these are among the most clinically important because they are common, dangerous, and treatable when recognized early. A high gap should prompt consideration of the exposure timeline, associated symptoms, and confirmatory testing.
How Toxic Alcohols substances Affect Acid-Base Balance
Harmful alcohols remain among the major sources of severe anion gap increase. This set includes methanol and ethylene glycol, all of which can initially appear deceptively mild before substantial metabolic injury develops. Their danger stems from metabolism into very acidic compounds.
These substances also often produce an higher osmolar gap early in the course. The osmolar gap indicates extra osmoles in the blood and can be valuable when a toxic ingestion is suspected. With time, as the parent alcohol is metabolized, the osmolar gap may fall while the anion gap rises. Such a pattern is a major diagnostic clue.
With methanol, the critical toxic metabolite is formic acid. Formic acid leads to metabolic acidosis and can harm the optic nerve, which is why visual symptoms may be important. With ethylene glycol, glycolic acid and related metabolites drive acidosis and renal injury.
The acid-base effect is not merely a lab curiosity. It reflects a genuine physiologic emergency in which toxic metabolites accumulate, buffering systems are overwhelmed, and the patient enters a worsening acidotic state. That is why treatment decisions often depend on the combination of symptoms, exposure history, blood gas results, and the gap pattern.
In some cases, a patient may have both an elevated osmolar gap and a high anion gap metabolic acidosis. That combination strongly supports toxic alcohol exposure and demands immediate action. However, neither number alone is sufficient to rule in or rule out the diagnosis.
Other Toxic Exposures and Disorders That Raise the Anion Gap
Not every high gap is caused by toxic alcohols. Many other processes can produce the same picture, including ketoacidosis, renal failure, uremia, and cyanide exposure. These conditions all cause acids to accumulate or reduce the body’s ability to clear them.
Ketoacidosis occurs when ketone production increases https://anion-gap-app099.iamarrows.com/what-does-an-anion-gap-of-20-mean more quickly than the body can use them. This can happen in diabetes, prolonged fasting, or heavy alcohol use. Ketones are organic acids, so they widen the gap and reduce bicarbonate levels.
Renal failure can also raise the gap because damaged kidneys cannot remove acids effectively. When waste products build up, uremia develops, and the patient can progress into metabolic acidosis. This is one reason kidney function is a component of the standard evaluation for unexplained acidosis.
Cyanide is particularly dangerous because it prevents cellular oxygen utilization. Even if oxygen is present in the blood, cells cannot use it properly, which can rapidly cause severe lactic acidosis. In this setting, the anion gap may rise as lactate accumulates.
This range of causes matter because a high gap is not exclusive to ingestion. It can also indicate internal illness, tissue hypoperfusion, or organ failure. The challenge is determining whether the pattern reflects a toxin-related emergency or another severe cause of acid-base disruption.
When a Normal Anion Gap Does Not Rule Out Poisoning
A normal anion gap does not rule out poisoning. This is especially true in early poisoning, when the toxic substance has not yet been fully metabolized into acidic byproducts. In that stage, the gap may still look normal even while the patient is declining clinically.
Another reason for a misleading result is a mixed acid-base disorder. For example, a patient may have one process increasing the gap and another process lowering it, producing a net value that appears deceptively normal. Nausea and vomiting, hyperventilation, renal disease, or treatment given before labs are drawn can all affect the final number.
That is why clinical suspicion remains crucial. Symptoms, timing, access to toxic substances, mental status, and lab trends matter more than a single snapshot. If the history suggests ingestion, clinicians should not dismiss the possibility simply because the anion gap is not elevated yet.
This point is especially important with toxic alcohols and salicylates, where the laboratory picture can evolve over time. Repeating labs may reveal a developing anion gap elevation even if the first sample is unrevealing.
In short, the gap is a helpful clue, but a normal result is not a guarantee of safety.

What Other Tests Are Used Alongside the Anion Gap?
In cases where toxin induced acid buildup is suspected, the anion gap is just one part of the workup. A blood gas helps assess pH, bicarbonate status, and whether the body is in an acidotic state. It can also show whether a respiratory component is present.
Serum lactate is commonly checked because high lactate can account for a high gap and point toward tissue hypoperfusion, fits, or toxin ingestion. Rising lactate may also signal significant cellular stress and increasing metabolic derangement.
Ketones are essential whenever ketoacidosis is possible. Checking ketones can help distinguish diabetic ketoacidosis, starvation ketosis, or alcohol-related ketosis from other reasons of metabolic acidosis.
A tox screen may be helpful as well, although standard screens do not detect every toxin. Specific testing for methanol, ethylene glycol, salicylates, or other substances may be needed based on the patient history and initial labs. For this reason targeted testing and indirect clues often work together.
Additional evaluations might include kidney function tests, osmolality tests, and repeated electrolyte panels. The purpose is to bring together the anion gap with the rest of the findings so the likely source can be identified quickly and treatment can begin.
When to Seek Urgent Medical Evaluation
Prompt assessment is required when toxin ingestion is possible and symptoms indicate serious illness. Warning signs include altered mental status, progressively worse breathing, intense vomiting, fainting, seizures, changes in vision, or unexplained confusion. Such findings may indicate a serious acid-base disorder or ongoing poisoning.
If ingestion is suspected for ingestion, call poison control without delay and obtain emergency care if symptoms are worsening. Immediate care can make a major difference in results for toxic alcohols, salicylates, cyanide, and other poisons.
Patients should not wait for warning signs to become intense if the exposure is recognized or strongly suspected. Prior to a definitive diagnosis is confirmed, the combination of clinical history, a high anion gap, and supportive lab findings can warrant immediate action.
A practical approach is to treat the anion gap as one piece of a larger picture. If the number is high, the patient may need additional testing and urgent management. If the number is not elevated but suspicion remains high, another review is still necessary because poisoning can progress rapidly.
FAQ
What toxins most commonly increase the anion gap?
The most common toxin-related causes include methanol, ethylene glycol, and salicylates. These can produce high anion gap metabolic acidosis through toxic metabolites, acid accumulation, or both. Severe lactic acidosis from poisoning or tissue injury can also raise the gap.
Can a normal anion gap still happen with poisoning?
Absolutely. A normal anion gap can occur in early poisoning or in a mixed acid-base disorder that masks the abnormality. If clinical suspicion is high, the patient may still need follow-up labs and targeted toxicology testing.
How does an Anion Gap Calculator help with toxin evaluation?
An Anion Gap Calculator rapidly uses the anion gap formula to the patient’s laboratory values. It helps identify whether the result is outside the expected reference interval, helps detect anion gap elevation, and can be paired with albumin correction for better laboratory interpretation.
What is the difference between anion gap and osmolar gap?
The anion gap calculates unmeasured anions and is useful for detecting metabolic acidosis. The osmolar gap calculates unmeasured osmoles and is especially helpful in suspected toxic alcohols. In some poisonings, the osmolar gap is high early, while the anion gap rises later as toxic metabolites such as formic acid and glycolic acid accumulate.
When should someone seek urgent care for suspected toxin exposure?
Get immediate medical attention at once for potential toxin poisoning with changed mental state, shortness of breath, fits, persistent vomiting, changes in vision, or passing out. Contact poison control right away as well. These symptoms may signal a critical acid-base disorder that needs prompt evaluation and management.