What this compound is and where it is present
Propylene glycol is a solvent and delivery agent used in a number of medical and nonmedical products. In clinical environments, it is most important because it can appear in IV medications, especially certain sedatives and other formulations that need a liquid base. It can also be present in some oral products and topical products. Most exposures are harmless, but large or prolonged exposure can create a toxicity problem, especially in hospitalized patients.
This is important because propylene glycol is not just an ingredient; it is a compound that is metabolized by the body into other substances. Under the right situations, those metabolites can affect acid-base balance and lead to abnormal serum chemistry findings. In some patients, the clinical picture includes high anion gap findings, especially when the exposure is significant or renal clearance is impaired.
From a diagnostic evaluation standpoint, propylene glycol exposure is often overlooked unless the medication list is reviewed closely. That is why laboratory interpretation must be paired with clinical correlation. The product source, route of exposure, and duration all influence whether propylene glycol becomes clinically relevant.
How the anion gap is determined
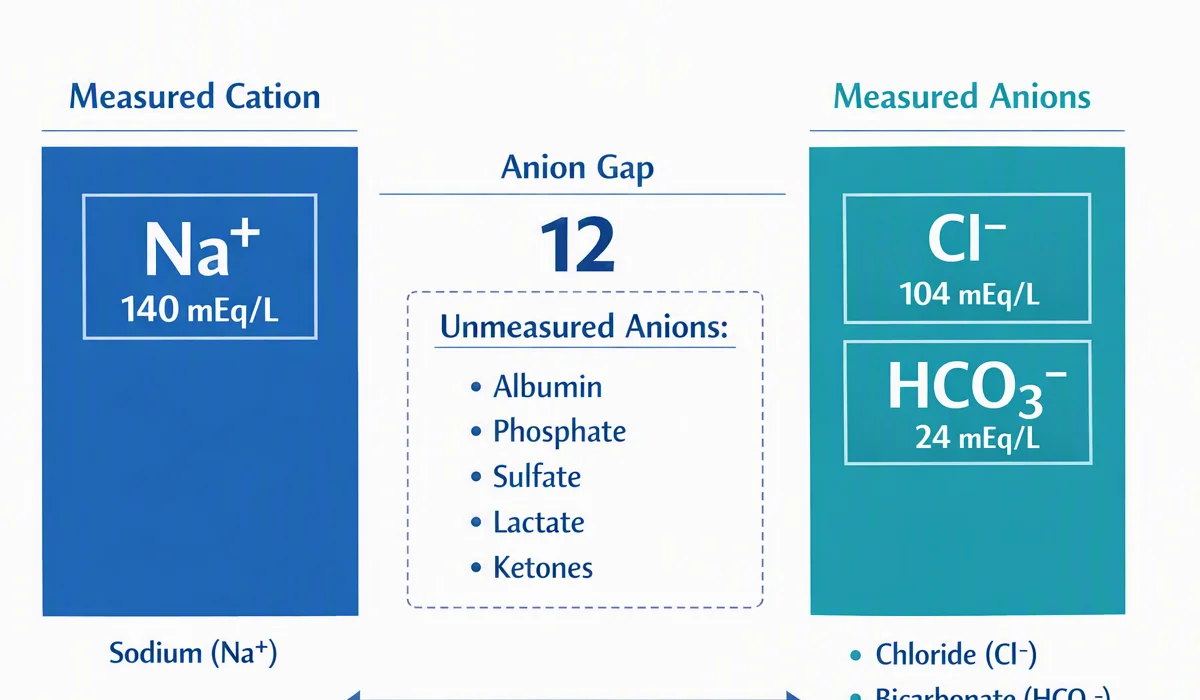
The anion gap is a calculated value used to detect certain forms of metabolic acidosis. It represents the variation between observed cations and tested anions in the blood. The most common anion gap formula uses serum sodium, serum chloride, and serum bicarbonate.
A basic version is:
anion gap = serum sodium − (serum chloride + serum bicarbonate)An anion gap calculator simplifies this calculation and can assist clinicians and patients understand whether the result sits in a normal span or suggests an acid-base imbalance. Because the result depends on the measured electrolyte values, even small electrolyte changes can change the number.
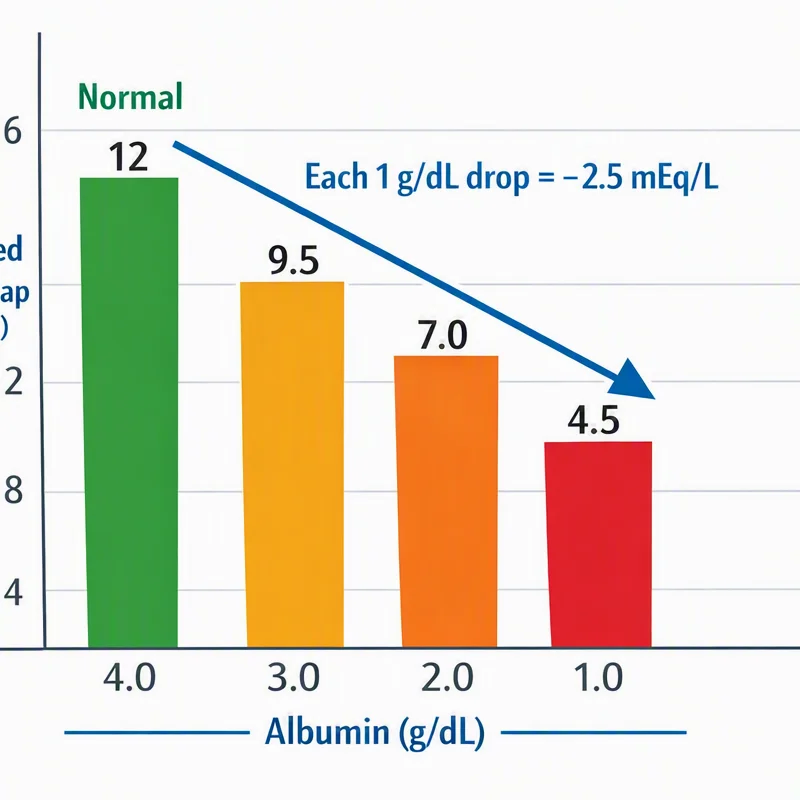
The anion gap is useful because unmeasured anions can increase in the blood during conditions such as lactic acidosis, ketoacidosis, or toxin ingestion. When interpreting the number, clinicians also consider albumin, since low albumin can reduce the measured gap and obscure a clinically important issue. That is why the albumin-corrected anion gap is often more revealing than the unadjusted value.
What makes propylene glycol can increase the anion gap
Indeed, propylene glycol can lead to a high anion gap in the setting of propylene glycol toxicity. The mechanism is usually secondary rather than sudden. After exposure, propylene glycol is broken down into acidic compounds, including organic acids, which can promote high anion gap metabolic acidosis. In addition, the body may develop a concurrent lactic acidosis, which additionally increases the gap.
Another important clue is the osmolar gap. Propylene glycol itself raises serum osmolarity, so early toxicity may present with an high osmolar gap before the anion gap rises. As metabolism continues, the parent compound falls while acidic metabolites accumulate, shifting the pattern from isolated osmolar gap elevation to a combined osmolar gap and high anion gap presentation.
This progression is why the timing of testing matters. A patient may initially have a high osmolar gap and later show increasing acidosis, elevated lactate, and a rising anion gap. In other words, propylene glycol can be part of a complex laboratory pattern that evolves over time.
Frequent causes of high anion gap metabolic acidosis
Propylene glycol is only one possible cause of metabolic acidosis. A wide differential diagnosis is crucial whenever the anion gap is elevated. Typical causes include ketoacidosis, lactic acidosis, renal failure, and ingestion of toxic alcohols. All of these can cause a similar lab pattern, but the underlying mechanism is different.
Ketoacidosis is often seen with diabetes, starvation, or prolonged vomiting, while lactic acidosis may occur with shock, sepsis, hypoperfusion, or certain drugs and toxins. Renal failure can raise the gap because the kidneys cannot clear acid effectively, allowing unmeasured acids to accumulate. Toxic alcohols, such as methanol or ethylene glycol, can also lead to an elevated anion gap and osmolar gap pattern.
This is why laboratory interpretation should never rely on a single number alone. The anion gap calculator can identify a abnormal result, but the final diagnosis depends on the clinical context, medication exposure, and additional testing.
Signs and symptoms of propylene glycol toxicity
The manifestations of propylene glycol toxicity can be unclear at first. Patients may present with altered mental status, hypotension, and tachypnea as the acid-base disturbance worsens. Tachypnea often reflects respiratory compensation for acidosis. Some patients may https://anion-gap-reference252.scriblorax.com/posts/anion-gap-calculator-equation-calculation-and-explanation also exhibit signs of worsening perfusion or sedation, depending on the overall exposure and the medications involved.
A rising serum lactate can be an important clue, especially when the clinical picture suggests an unexplained acid-base problem. Elevated lactate does not prove propylene glycol as the cause, but it raises concern when combined with medication exposure, abnormal serum chemistry, and a high anion gap. Because the signs overlap with other illnesses, clinical correlation is critical.

Severe cases can deteriorate fast, particularly when the patient has reduced clearance or multiple risk factors. A careful review of medications, infusion history, and serial labs is often the best way to recognize the problem.
Tests used to evaluate suspected poisoning
If propylene glycol intoxication is suspected, the workup usually includes serum osmolality, determination of the osmolar gap, a blood gas, and evaluation of renal function. These studies help determine whether the patient has a combined toxic and metabolic pattern.
Serum osmolality is compared with the calculated osmolarity to identify an osmolar gap. An elevated gap suggests unmeasured osmotically active substances, which may include propylene glycol or other toxic alcohols. The blood gas helps define the severity of the acid-base disorder and shows whether the patient has metabolic acidosis with respiratory compensation. Renal function testing is important because reduced clearance can worsen toxicity and prolong exposure.
Additional labs often include serum lactate, electrolytes, and repeat chemistry panels. Serial testing can show whether the anion gap is rising or resolving after intervention. In many patients, the pattern of serum chemistry abnormalities provides the strongest evidence before specialized toxin levels are available.
How to interpret an Anion Gap Calculator result
An anion gap calculator is useful, but the result should always be interpreted in light of the clinical picture. First, confirm whether the value is in the normal range for the laboratory used. Normal ranges can shift somewhat depending on the analyzer and whether potassium is included in the formula. A result that is borderline in one lab may be clearly abnormal in another.
Next, evaluate the possibility of hypoalbuminemia. As albumin is a major unmeasured anion, low albumin can mask a true acidosis. An albumin-corrected anion gap gives a better estimate of the underlying acid burden when albumin is reduced. This adjustment is particularly helpful in critically ill patients, where albumin is often low.
Lastly, ask whether the result corresponds to the overall picture. A high anion gap with normal lactate and normal ketones may point toward a toxin, while a high gap with elevated lactate may indicate tissue hypoperfusion, sepsis, or propylene glycol toxicity. Good interpretation depends on clinical context, not just the number.
When propylene glycol exposure becomes hazardous
The risk rises with dose-related toxicity, prolonged exposure, and decreased ability to remove the compound. This is particularly important with some benzodiazepines and other intravenous medications that use propylene glycol as a solvent. Continuous, high-dose infusion can cause buildup over time.
Renal impairment raises risk because the kidneys have a key role in removing the compound and its byproducts. If renal clearance is reduced, propylene glycol and its metabolites may build up, pushing the patient toward osmolar gap elevation, lactic acidosis, and high anion gap metabolic acidosis.
Risk is highest when multiple factors come together: high medication dose, prolonged infusion, critical illness, dehydration, and impaired kidney function. In that setting, monitoring should be more regular and clinicians should keep a high level of suspicion for toxicity.
Treatment and management of suspected propylene glycol toxicity
The first step in management is discontinuation of the suspected source. Discontinuing the offending medication or exposure can avoid more accumulation. Depending on the severity of the case, the patient may also need supportive care, including fluid resuscitation, correction of electrolyte abnormalities, and treatment of acidosis.
Monitoring is crucial after the exposure is stopped. Serial serum chemistry testing, blood gas assessment, serum lactate, and renal function checks help show whether the acid-base disorder is resolving. If the patient has severe symptoms, rapidly worsening acidosis, or significant renal dysfunction, more aggressive treatment may be needed.
Hemodialysis can be considered in severe cases because it helps remove propylene glycol and correct associated metabolic derangements. It may be especially useful when there is significant acidosis, hemodynamic instability, or impaired renal clearance. The decision is based on the full clinical picture rather than the anion gap alone.
When to seek urgent medical evaluation
Prompt evaluation is warranted if there are acute danger signs such as increasing confusion, marked weakness, respiratory distress, collapse, or shock symptoms. A patient with suspected toxic exposure and a suddenly worsening condition should not wait for routine follow-up.
Concerning features include severe acidosis, very low bicarbonate, sustained hypotension, or fast-rising lactate. These findings may signal a serious acid-base disorder that needs immediate treatment. If propylene glycol exposure is possible, a prompt medical assessment can clarify whether the patient needs hospital monitoring, medication changes, or hemodialysis.
Since this condition can overlap with other causes of high anion gap metabolic acidosis, clinicians should evaluate the whole picture early. Early review of medication exposure, serum osmolality, blood gas results, and renal function can prevent delays in care.
Frequently asked questions about propylene glycol and the anion gap
Can propylene glycol cause a high anion gap?
Yes. Propylene glycol can cause a high anion gap, especially when exposure is significant or prolonged. It may first raise the osmolar gap and then, as it is metabolized into acidic metabolites, contribute to high anion gap metabolic acidosis and lactic acidosis.
What is the difference between an anion gap and an osmolar gap?
The anion gap represents unmeasured charged particles and helps recognize causes of metabolic acidosis. The osmolar gap shows the difference between measured and calculated osmolarity and suggests unmeasured dissolved substances, such as propylene glycol or other toxic alcohols. Both are helpful, but they address different questions.
Which medications contain propylene glycol?
Propylene glycol can be found in some intravenous medications, including certain benzodiazepines, sedatives, and other formulations that use it as a solvent. It may also appear in some oral products and topical products. The exact formulation depends on the drug and manufacturer, so the medication list should be checked carefully.
What indications may indicate propylene glycol toxicity?
Possible signs include confusion, low blood pressure, increased respiratory rate, and signs of progressive acidosis. A rising serum lactate may also be noted. As these findings are not specific, they must be assessed with exposure history, lab values, and general clinical correlation.
How is propylene glycol toxicity treated?
Treatment usually starts with discontinuation of the source and supportive care. Clinicians observe the patient closely with repeat labs, including blood gas, serum chemistry, and renal function. In critical cases, hemodialysis may be used to clear the toxin and improve severe acidosis.